Types of Abortion
Medication Abortion, Procedural Abortion, and Self-Managed Abortion
An essential initial step in advocating for Midwives, Nurse Practitioners (NPs), and Physician Associates (PAs) as abortion providers involves comprehensive education regarding abortion care. Often, politicians, regulators, and healthcare practitioners lack awareness of the fundamental training required to become proficient providers of medication or procedural abortion. This knowledge gap can contribute to stigma and uninformed decisions that unjustly restrict Advanced Practice Clinician (APC) training and limit abortion access.
Many factors may influence the type of abortion a patient needs or prefers. Gestational duration is one factor, and certain medication regimens or procedural options may be limited by gestation. Other factors that can impact how, when, or under what circumstances a patient may seek care earlier or later in pregnancy can include difficulties accessing care near their home, privacy within families for adolescents or those experiencing domestic violence, pregnancy as a result of rape, queer people who are unsafe in their homes or communities, and lack of access to adequate financing and childcare, among other factors. In cases where a patient could choose either medication or procedural abortion, the decision between the two options may be based on privacy or other personal preferences.
While abortion care can take many forms, this Toolkit concentrates on the two methods predominantly utilized during early pregnancy: medication and procedural abortion. The overwhelming majority of patients seeking abortion care do so before 14wks gestation, the period during which APCs are most frequently engaged in providing such care. It's imperative to recognize that Advanced Practice Clinicians (APCs) can, depending on state laws, offer abortion care across all gestations, including midwives who provide labor induction abortion in later gestations. (Future versions of this toolkit will discuss this more in-depth.)
Early abortion
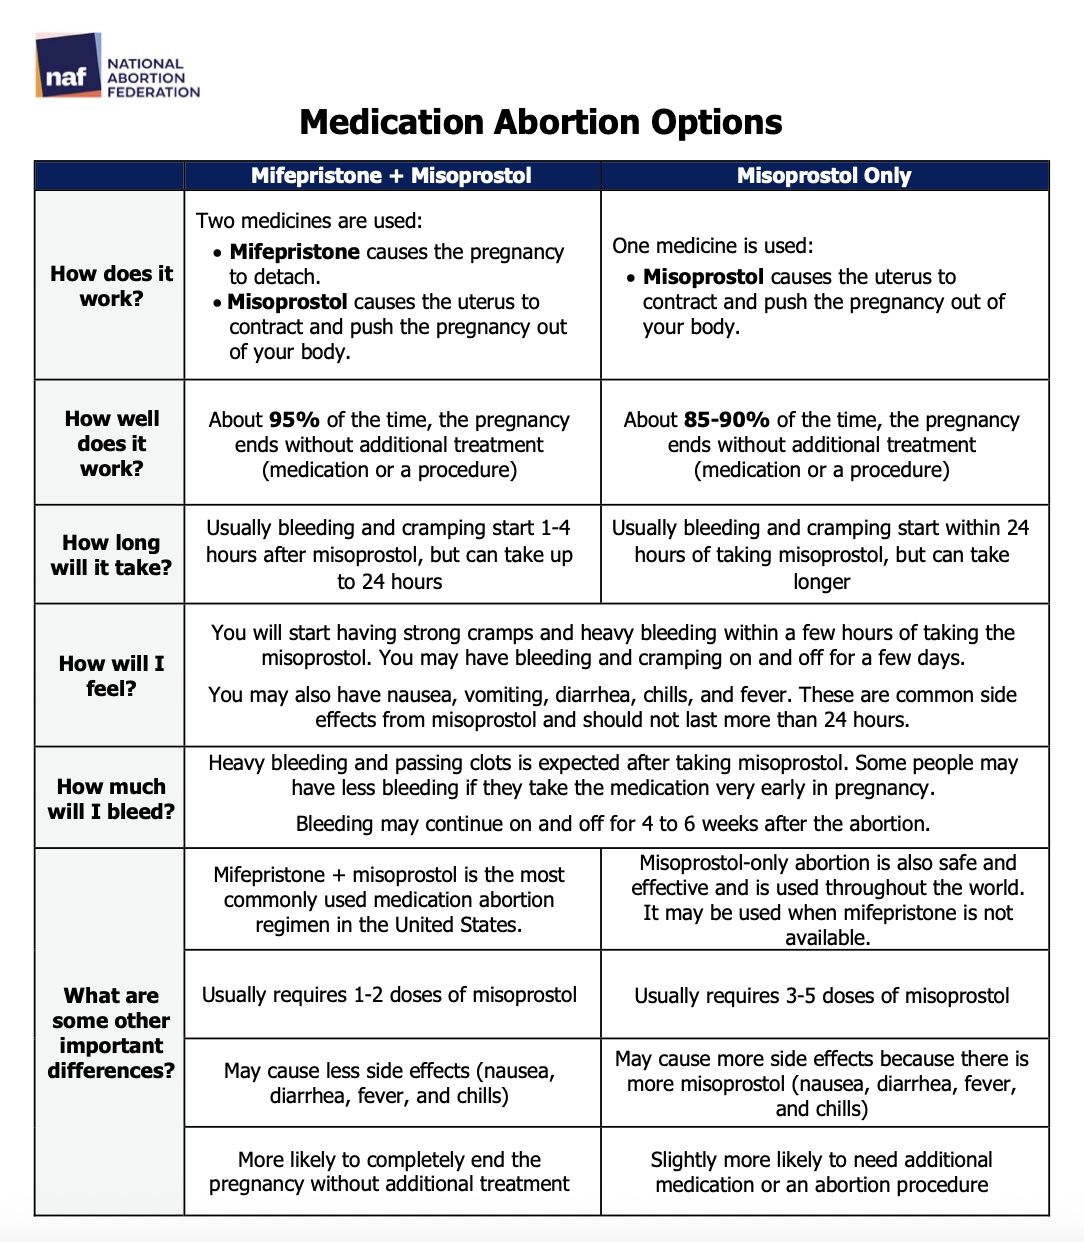
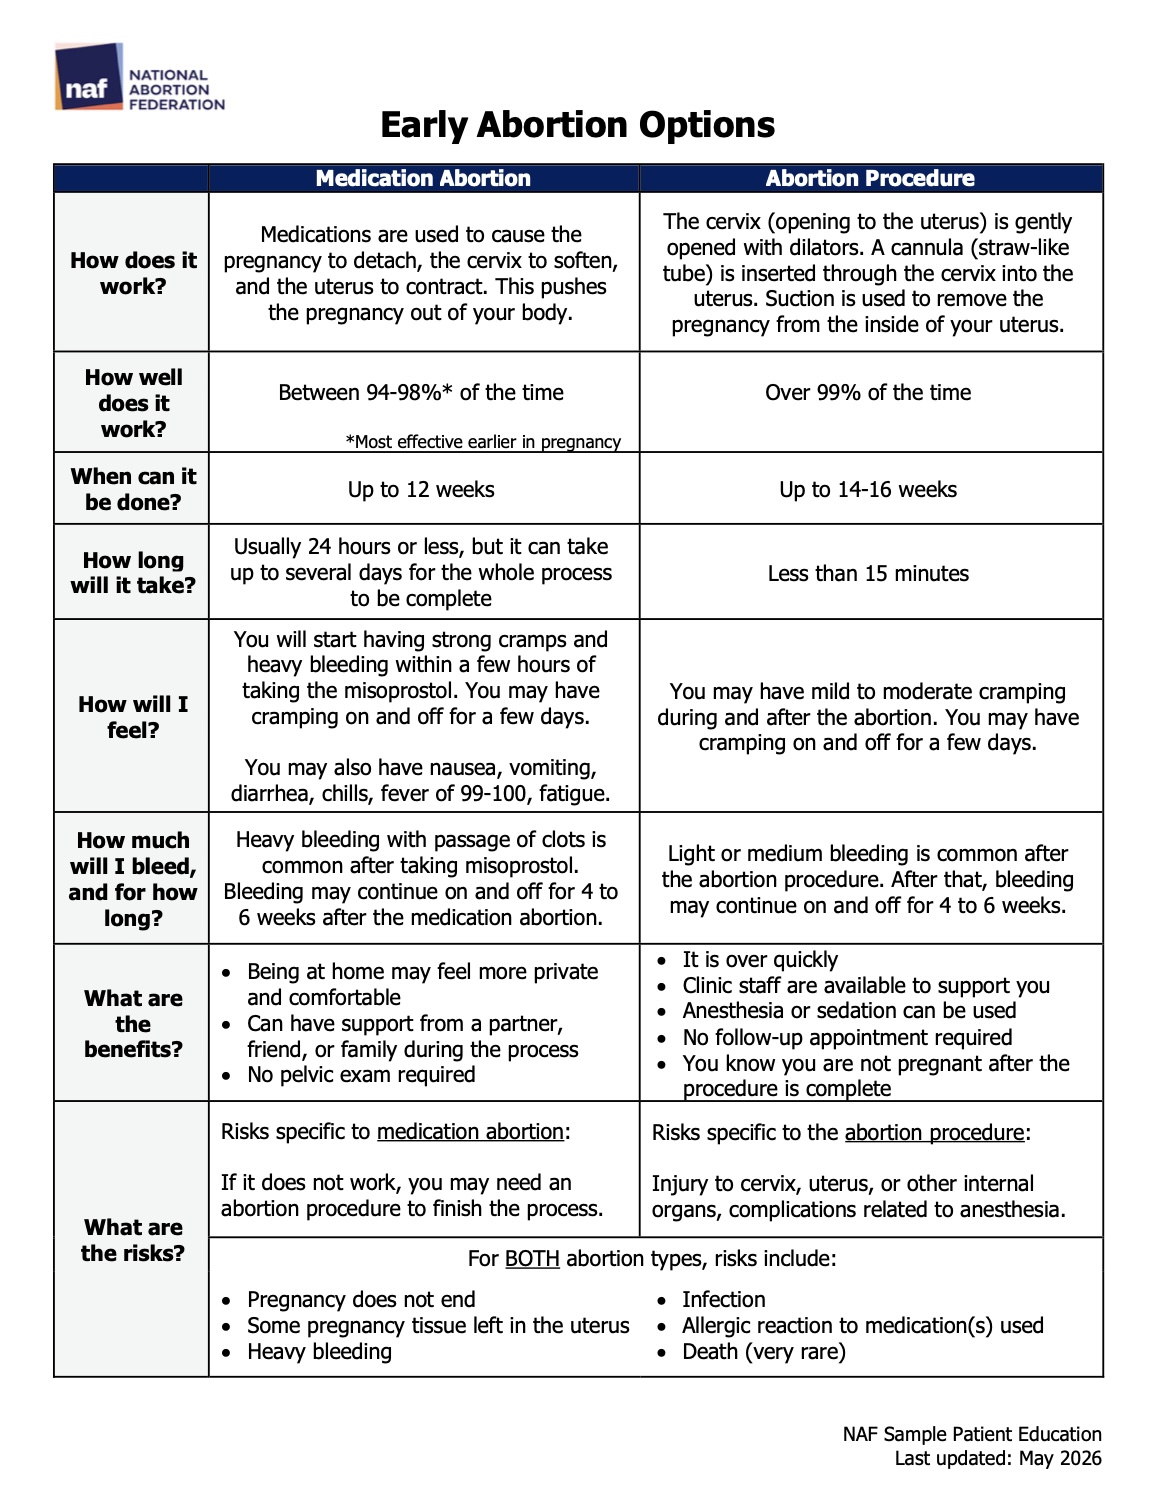
Early abortion options include medication abortion and procedural abortion. We have included a NAF Early Abortion Options side-by-side comparison table below. These options can also both be provided in-clinic or, in the case of medication abortion, can be provided via telehealth with pills shipped to a patient's home. While medication abortion provided through either in-clinic or telehealth abortion differs from self-managed abortion in how the pills are obtained, the pill regimens do not. Information on abortion pill regimens can be found below in the Self-Managed Abortion section, and most typically involve a regimen of mifepristone and misoprostol, but also may be misoprostol-only.
Mifepristone was approved by the FDA in 2000, and 26 years of US data has supported the safety and efficacy of this regimen, whether through in-clinic administration or via telehealth. Misoprostol-only medication abortion is the most common regimen globally, and data on the safety and efficacy of the misoprostol-only regimen can be seen here and at the World Health Organization (WHO) website.
Additional alternative medication abortion regimens studies are currently underway with medications such as ulipristil and methotrexate. As we obtain more data on these studies, they will be linked in future versions of this toolkit.
See here for a Telehealth For Abortion Care & Advanced Practice Clinicians (APCs): Key Aspects Of Expanding Access To Care factsheet.
For more information on in-clinic options, including medication and procedural abortion, please see this page from the National Abortion Federation website Abortion in Clinic: What to Expect.
“Procedural” Versus “Surgical”: What’s in a Name?
The terminology employed in discussions about abortion plays a significant role in shaping perceptions. Referring to procedures as "procedural" rather than "surgical" can help dispel misconceptions surrounding abortion care. The term "surgical" erroneously implies a more complex level of care typically associated with surgeons and hospitals. Conversely, "procedural abortion" accurately reflects the nature of early abortion techniques, which are often straightforward and can be conducted using basic analgesics in primary care settings. Not only is the term procedural abortion clarifying, but it can also challenge the thinking that only physicians should provide abortion care and that this care needs to take place in more complex settings.
Primary care providers, including APCs, routinely perform a range of procedures, such as intrauterine device (IUD) insertion, endometrial biopsy, management of early pregnancy loss, and abortion. Adopting the terms "procedural" abortion instead of "surgical" abortion constitutes small yet significant steps in demystifying early abortion techniques. More information about abortion nomenclature can be found on the Advocacy page of this toolkit under the 'Language Matters' header.
Later Abortion Care
Abortion care later in pregnancy is, by definition, rarer than other abortions. Most later abortions are performed in an out-patient setting using a combination of medication (mifepristone and misoprostol), feticidal injection depending on gestation, followed by dilation & evacuation (D&E) or induction of labor (IOL). Before 24 weeks of pregnancy, D&E has been shown to be safer than IOL, though either approach may be used, depending on patient and provider preference (Pettit, et al., 2017). Induced fetal demise by transabdominal or transcervical injection of digoxin/lidocaine/KCl is routinely performed starting at 24 weeks and beyond (Diedrich, et al., 2024).
Media, cultural, and political narratives about later abortion are often inaccurate, misleading, and dangerous. Terminology like “post-birth,” “partial-birth,” or “born-alive” abortions intentionally distort the public’s understanding about the relative safety and effectiveness of these procedures. All abortions–regardless of when the care is provided–are either “spontaneous” or “induced,” “medication” or “procedural.” Referring to later abortions otherwise, or in terms of “viability” or “medical necessity,” fuels stigma and perpetuates anti-scientific, non evidence-based narratives about procedures that can already be emotionally and physically difficult for patients. (Heuser, et al., 2022).
Likewise, rhetoric about the purported dangers of later abortion care are often unsupported by the data. While abortion after 20 weeks carries more risk than that of abortion in early pregnancy, the most recent 2022 CDC findings report overall mortality related to abortion to be 0.46 deaths per 100,000 procedures–the lowest rate since 1973 (Ramer, S., et al.; 2024). When compared to induced abortion, the mortality risk of staying pregnant in the United States is estimated to be 35-39 (Stevenson, A; Raymond, E; Grossman, D; 2024) times higher, making later abortion a safer alternative. Abortion access across all stages of pregnancy leads to safer outcomes for patients.
Self-Managed Abortion
Self-managed abortion (SMA) is a common way for people to terminate their pregnancies. Described by Abortion On Our Own Terms, in SMA, "people obtain medications outside the formal health care system – from online sources or community networks and use them to self-manage their care. Unfortunately, in the current hostile environment, self-managing an abortion comes with legal risks on top of the logistical barriers." People choose SMA for a variety of reasons and use a variety of methods. Post-Dobbs, many people are choosing to self-manage their abortion at home with pills.
Abortion On Our Own Terms has an interactive website describing various methods of self-managed abortion and barriers to and criminalization of SMA. We Testify also has detailed information on SMA with pills.
If/When/How has compiled a fact sheet on self-managed abortion and healthcare professionals’ reporting responsibilities.
For more information on Self-managed abortion please see this page from the National Abortion Federation website Using Abortion Pills on Your Own: What to Expect